Pentadecanoic acid, written in shorthand as C15:0, is a 15-carbon saturated fatty acid that occurs naturally in full-fat dairy products and the fat of ruminant animals such as beef and lamb. Unlike the even-chain saturated fats that dominate most dietary discussions, C15 belongs to a less-studied class called odd-chain fatty acids, which the body handles somewhat differently at a metabolic level.
Interest in C15 has grown in recent years largely because of research from a group of scientists at the biotechnology company Epitracker, who have proposed that this fatty acid may support cellular health through several distinct mechanisms. Their hypothesis, that C15 might be considered an essential fatty acid for humans, remains preliminary and has not been formally adopted by regulatory bodies or mainstream nutrition organizations. What follows is an honest summary of what C15 is and what current science suggests, without overstating a field that is still in early stages.
Key Takeaways
- C15 is a 15-carbon saturated odd-chain fatty acid found primarily in full-fat dairy products and ruminant animal fat.
- Proposed mechanisms include cell membrane stabilization, partial PPAR-α/δ receptor agonism, and potential effects on ferroptosis and cellular senescence: all of which remain early-stage hypotheses.
- The classification of C15 as an ‘essential’ fatty acid is a hypothesis from Epitracker researchers; it has not been formally adopted by the FDA or mainstream nutrition science bodies.
- Supplemental C15 had no significant adverse events in the one small 200 mg/day trial[1], which was supported by the supplement maker and ran only 12 weeks, so long-term safety data does not yet exist [1].
- This is a developing area of nutritional science worth monitoring, but current evidence does not support treating C15 as a proven remedy for any specific health condition.
The Chemistry of C15:0
Pentadecanoic acid is a straight-chain, fully saturated fatty acid with 15 carbon atoms. The ‘0’ in C15:0 indicates zero double bonds, meaning every carbon in its chain is fully bonded to hydrogen atoms. This distinguishes it from unsaturated fatty acids like oleic acid (C18:1) or omega-3s, which contain one or more double bonds that introduce kinks into their structure.
Odd-chain fatty acids like C15:0 are produced in small quantities by the forestomach bacteria of ruminants during fermentation of plant fiber. When ruminant animals such as cows, goats, or sheep consume grass and hay, their gut microbes synthesize these odd-chain fats, which then deposit into the animal’s milk fat and body fat. This is why full-fat dairy (butter, whole milk, aged cheese) is among the most consistent dietary sources of C15 for humans.
Most human C15 is thought to come from diet, but whether the body makes enough is unsettled: an independent review calls essentiality controversial and says more work is needed [4]. It is not, however, absent from human metabolism. The documented endogenous route runs through propionate: propionic acid produced by gut bacteria fermenting dietary fiber is converted to propionyl-CoA and elongated into odd-chain fatty acids, but evidence is split: inulin fiber raised plasma C15 by about 17% in one small crossover trial, two other small human studies found no rise, and in 869 Dutch heart attack survivors C15 tracked dairy but not fiber [6][15][16]. That distinction matters when reading the essentiality argument, because the question is not whether the body can make C15 at all, but whether it can make enough.
Cell work suggests a third route besides diet and fiber. In 3T3-L1 mouse adipocytes grown under standard culture conditions, 13C-labeling experiments showed that propionyl-CoA acts as the primer on fatty acid synthase for odd-chain fatty acids such as C15:0 and C17:0, and that valine and isoleucine were the main source of the propionyl-CoA pool [14]. That points to branched-chain amino acid breakdown as a possible source of C15 in fat cells. It is a result in a mouse cell line, so it shows the pathway exists in those cells, not how much of anyone’s blood C15 comes from protein.
Where C15 Is Found in Food
The richest natural sources of C15 are full-fat dairy products. Butter, whole cow’s milk, cream, and aged hard cheeses contain the highest concentrations. The fatty acid profile of dairy varies depending on the animal’s breed, diet, and season: grass-fed ruminants generally produce milk with higher odd-chain fatty acid content than grain-fed counterparts.
C15 is about 1 percent of the fat in milk, and freshwater fish carry it too
C15 is a minor component of dairy fat, and dairy is not its only food source.
Percent of total fatty acids, from a narrative review of milk and fish figures; cow-to-cow variation from a separate small study. Source: British Journal of Nutrition 2022; BMC Genomics 2026.
Data table
| Item | Value |
|---|---|
| Cow's milk, C15:0, share of total fatty acids | 1.0% |
| Cow's milk, C17:0 | 0.5% |
| Freshwater fish, C15:0 | 0.4% |
| Freshwater fish, C17:0 | 0.6% |
Chart: c15hub.com: C15 is about 1 percent of the fat in milk, and freshwater fish carry it too
Embed this chart
Free to reuse on your site. Copy the code below; please keep the credit link.
Research note: In French women of the E3N cohort, serum pentadecanoic acid tracked dairy product intake reported years earlier, supporting it as a marker of usual dairy intake [25].
Freshwater fish also carry C15 at about 0.4% of their fatty acids (versus about 1% in milk fat), and in a Chinese cohort blood odd-chain levels tracked wheat, coarse grains and fish as well as dairy [17][18]. Dairy fat remains the most practical and best-studied dietary source for most people in Western countries. Individuals who avoid all animal products or follow strict low-fat diets will typically have lower circulating levels of C15, which is part of what motivated researchers to develop C15 supplements as an alternative delivery route.

It is worth noting that C15 is just one component of a complex fat matrix. Eating full-fat dairy for its C15 content also means consuming other saturated fats, calories, and nutrients. Whether the benefits proposed for isolated C15 supplementation apply equally to whole-food dairy consumption is not yet established.
Proposed Mechanisms: How C15 May Work in Cells
Researchers have proposed several mechanisms by which C15 might influence cellular health. The first is structural: like other fatty acids, C15 can incorporate into cell membranes, where its odd-chain length may confer a different kind of rigidity or fluidity compared to even-chain saturated fats. Epitracker scientists have suggested this membrane integration may help stabilize cells and reduce what they call ‘cellular fragility.’
A second proposed mechanism involves nuclear receptors. C15 is reported to act as a partial agonist of peroxisome proliferator-activated receptors alpha and delta (PPAR-α and PPAR-δ). These receptors regulate genes involved in fatty acid oxidation, mitochondrial function, and inflammation. Partial agonism, as opposed to full agonism, means the fatty acid may activate these receptors at a more moderate level than pharmaceutical PPAR agonists, which have historically carried safety concerns.
Two additional cellular-level hypotheses have been raised: that C15 may help reduce ferroptosis, a form of iron-dependent regulated cell death linked to lipid oxidation, and that it may reduce cellular senescence, the state in which cells stop dividing but remain metabolically active and can secrete pro-inflammatory signals. Much of this work is company-affiliated and was done in cultured cells rather than in people[7][3]. Both are areas of active general research in aging science, and C15’s role within them is speculative and early-stage.
The 'Essential Fatty Acid' Hypothesis
The claim most associated with C15 in popular media is that it is a newly discovered essential fatty acid, meaning the body cannot make enough of it on its own and must obtain adequate amounts from diet. This hypothesis originates primarily from Epitracker-affiliated researchers and has been published in peer-reviewed journals. However, the classification of C15 as ‘essential’ in the formal nutritional sense has not been adopted by the U.S. Food and Drug Administration, the European Food Safety Authority, or major nutrition bodies such as the National Academies of Sciences.
To be classified as essential, a nutrient typically needs a demonstrated deficiency syndrome in otherwise healthy individuals consuming a diet lacking it, along with consistent evidence that repletion resolves that syndrome. C15 has not cleared that bar in humans. The closest experimental support comes from rats: an independent INRAE group in France fed essential-fatty-acid-deficient rats and found that adding C15 at weaning partly restored growth, alongside the previously undescribed synthesis of odd-chain n-8 polyunsaturated fats[8]. That is a real result from a group with no commercial stake in it, and it is still a rodent result. In humans, the research shows an association between higher circulating C15 and lower type 2 diabetes risk, but other associations point the other way, such as lower lean mass in Mendelian randomization studies[9][19][20], and even that carries a caveat: analysts have questioned how reliably 15:0 works as a dairy-fat biomarker at all, which complicates any causal reading of the cohort data[10]. Association is not established essentiality.

This nuance matters for consumers. The science is genuinely interesting and worth following. But describing C15 as proven essential overstates what the current body of evidence supports.

How C15 Compares With Omega-3s and Other Fatty Acids
The established essential fatty acids are linoleic acid (omega-6) and alpha-linolenic acid (omega-3), which the body cannot make and must get from food. Medium-chain triglycerides and stearic acid are not essential. C15 sits in a separate group: an odd-chain saturated fat that dairy supplies, whose essentiality is still a hypothesis.
| Fatty acid | Type | Main dietary sources | Status as an essential fatty acid |
|---|---|---|---|
| C15:0 (pentadecanoic acid) | Odd-chain saturated | Full-fat dairy, ruminant fat | Proposed, not adopted by regulators |
| EPA and DHA (omega-3) | Long-chain polyunsaturated | Fatty fish, fish oil, algae oil | Omega-3 family is essential (alpha-linolenic acid) |
| Linoleic acid (omega-6) | Polyunsaturated | Vegetable oils, nuts, seeds | Essential |
| MCTs (C8, C10) | Medium-chain saturated | Coconut oil, MCT oil | Not essential |
| Stearic acid (C18:0) | Even-chain saturated | Beef, cocoa butter | Not essential |
Odd-chain fats also differ in how they are broken down. Beta-oxidation of an even-chain fatty acid yields only acetyl-CoA, while an odd-chain fatty acid such as C15 also yields one propionyl-CoA, which is the same propionate pathway described above.[5]
The most direct comparison with omega-3s is a cell-based study that tested C15 against EPA across 12 primary human cell systems. C15 was non-cytotoxic at every concentration tested [13], while EPA was cytotoxic to four cell systems at 50 µM. At 17 µM the two shared 12 activities, and C15 showed 28 additional activities, mostly anti-inflammatory, that EPA did not.[13] This was done in cultured cells, not people, and the authors disclose patents owned by the U.S. Navy or Epitracker and licensed to a company that sells a C15 supplement.[13] It shows C15 is not interchangeable with omega-3s in the dish. It does not show that C15 outperforms fish oil in a person, and no human trial has compared them.
C15 Supplements: Doses and Tolerability
Supplemental C15 is sold primarily under the brand name Fatty15, developed by Epitracker. Published human research has used 200 mg per day; [1] the UC San Diego randomized trial used 200 mg/day for 12 weeks and listed safety and tolerability among its stated objectives[1]. At these doses no serious adverse events were reported, in that trial or in the 12-week TANGO trial[2]. What has not been tested is anything longer. Twelve weeks is the outer edge of the published safety record, and no trial has tested a higher dose.
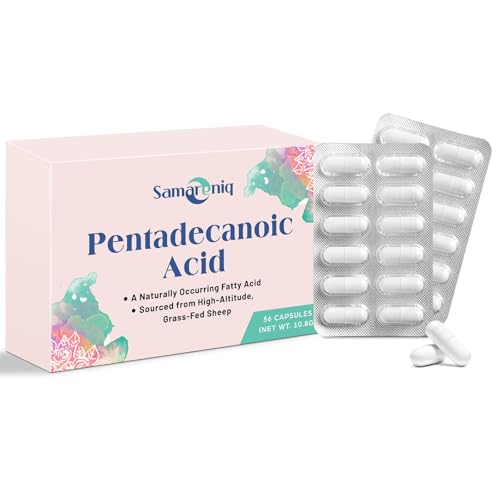
The FDA has not evaluated C15 supplements for any disease treatment or prevention. Like most dietary supplements sold in the United States, they are regulated under DSHEA (the Dietary Supplement Health and Education Act), which does not require pre-market safety or efficacy approval. This means the burden of evidence for therapeutic claims is much lower than for pharmaceutical drugs.
People with fish or dairy allergies, those on lipid-altering medications, those who are pregnant or breastfeeding, or those managing any chronic health condition should consult a physician before adding C15 supplements to their routine. The interaction profile of C15 with medications has not been systematically studied.
What the Research Does and Does Not Show
The published evidence on C15 falls into three groups, and they are not equally strong. The largest is observational. A pooled analysis of 16 prospective cohorts across 12 countries, covering 63,682 participants, found higher circulating 15:0 tracking with lower incidence of type 2 diabetes, at a hazard ratio of 0.80 across the 10th-to-90th percentile range [9]. Smaller observational work points the same way, including a borderline inverse association between plasma C15 and liver fat in 237 children (P = 0.048, which the authors call hypothesis-generating)[11]. The second group is mechanistic, largely cell-based or animal work[7][8], which does not automatically translate to humans. The third is supplementation trials, and there are two of them, not one.
The first randomized 30 young adults with overweight or obesity to 200 mg/day of C15 or placebo for 12 weeks. It was designed mainly to confirm that supplementation raises circulating C15 and to check safety, which it did[1]. The second, TANGO, is the more informative trial and the one least often quoted. Eighty-eight women with fatty liver disease were randomized to an Asian-adapted Mediterranean diet with C15, the same diet without it, or their habitual diet. Liver fat fell 33%, 30% and 10% across those three arms[2]. Almost all of the liver benefit tracked the diet, not the supplement. C15 did produce a further reduction in LDL cholesterol, which is a real finding, and a much narrower one than the way this trial is usually cited.
The first trial was supported by Seraphina Therapeutics, which supplied the capsules, and apart from a drop in the liver enzyme GGT it found no significant changes in any secondary outcome versus placebo [1].
Independent replication is the point most often misstated about this field, and it is usually misstated in the supplement’s favor. It is not true that the research is confined to one company: the pooled cohort analysis, the TANGO trial, the propionate-pathway work and the essentiality reviews all come from unaffiliated groups in Europe, Asia and North America. What is true is less flattering. When independent investigators set out specifically to test causality rather than association, using 3,196 CARDIA participants, a replication cohort of 3,889 in ARIC, and two-sample Mendelian randomization, they concluded that the collective evidence is not consistent with a causal cardiovascular benefit of C15[12]. Independent work exists. The strongest of it, so far, has not confirmed causality.
Some findings run the other way: genetically higher C15 was linked to lower appendicular lean mass in two Mendelian randomization studies, and higher C15 in red blood cells was seen in small-for-gestational-age babies [19][20][24].
Cell culture findings and rodent studies, which make up a significant portion of the mechanistic work, do not automatically translate to equivalent effects in humans. Many compounds show promising activity in isolated cells or animals and do not perform similarly in clinical trials. This is a standard limitation of early-stage nutritional science, not a specific criticism of C15 research.
The honest summary is this: C15 is a real, identifiable fatty acid with plausible mechanisms, a sizeable observational association with lower type 2 diabetes risk, though results vary between studies and are not uniformly favorable [21][22][23], and two short randomized trials whose results were modest and, in TANGO’s case, mostly attributable to the diet rather than the supplement. The causality tests so far have not found a benefit: CARDIA/ARIC found none for cardiovascular outcomes, and two Mendelian randomization studies linked higher C15 to lower lean mass[12][19][20]. It is not a proven treatment for any disease. The field is worth following, and the case for it is currently weaker than the marketing around it suggests.

🛒 Where to Buy Pentadecanoic Acid (C15)
- Fatty15 (official site) 20% off with code SFKKDBQQ
capsules, 100 mg C15 per capsule; 1 capsule/day starter, 2 capsules/day maintenance: Category creator, from the original Epitracker research team (Venn-Watson et al.); uses a patented, sustainably-sourced pure C15 ingredient; most expensive per-capsule but reference product for all comparisons - Double Wood Supplements Pentadecanoic Acid C15
capsules, 200 mg C15 per serving (2 capsules): Generic C15 supplement; significantly lower price than Fatty15; no independent clinical trials on this specific product; good option for budget-conscious buyers who want to trial the fatty acid - Sports Research Pentadecanoic Acid C15
softgels, 100 mg C15 per softgel: Established supplement brand with strong Amazon presence; softgel form may aid fat-soluble absorption; competitively priced mid-tier option - BulkSupplements Pentadecanoic Acid Powder (C15)
powder, 100 to 300 mg per measured serving: Most economical option for higher-dose protocols or stackers; requires a milligram-accurate scale; no excipients or additives; not recommended for beginners unfamiliar with powder dosing
As an Amazon Associate we earn from qualifying purchases. C15 products vary widely in how much pentadecanoic acid they actually contain, so check that the Supplement Facts panel lists C15 in milligrams as its own line item rather than bundling it into a fatty acid blend, and compare the per-serving dose with the 200 mg a day used in the one small published human trial [1].

A Note on the Evidence
The research on C15 is early-stage. The proposal that it is an essential fatty acid originates with researchers affiliated with the company that sells it, and while independent groups have since published on C15, the strongest independent test of causality to date did not support a causal cardiovascular benefit[12]. No C15 supplement has been evaluated by the FDA for any disease, and this article is informational only, not a substitute for personalized medical advice from a qualified healthcare provider.
References
- Pentadecanoic Acid Supplementation in Young Adults with Overweight and Obesity: A Randomized Controlled Trial. The Journal of Nutrition, 2024 (randomized trial)
- Effect of an Asian-adapted Mediterranean diet and pentadecanoic acid on fatty liver disease: the TANGO randomized controlled trial. The American Journal of Clinical Nutrition, 2024 (randomized trial)
- Efficacy of dietary odd-chain saturated fatty acid pentadecanoic acid parallels broad associated health benefits in humans: could it be essential?. Scientific Reports, 2020
- New insights on pentadecanoic acid with special focus on its controversial essentiality: A mini-review. Biochimie, 2024 (review)
- Pentadecanoic and Heptadecanoic Acids: Multifaceted Odd-Chain Fatty Acids. Advances in Nutrition, 2016 (review)
- Odd-chain fatty acids as a biomarker for dietary fiber intake: a novel pathway for endogenous production from propionate. The American Journal of Clinical Nutrition, 2017 (randomized trial)
- Pentadecanoic Acid (C15:0), an Essential Fatty Acid, Shares Clinically Relevant Cell-Based Activities with Leading Longevity-Enhancing Compounds. Nutrients, 2023 (cell-based study)
- Dietary pentadecanoic acid supplementation at weaning in essential fatty acid-deficient rats shed light on the new family of odd-chain n-8 PUFAs. The Journal of Nutritional Biochemistry, 2025 (animal study)
- Fatty acid biomarkers of dairy fat consumption and incidence of type 2 diabetes: A pooled analysis of prospective cohort studies. PLOS Medicine, 2018 (pooled analysis, 16 cohorts)
- Concerns about the use of 15:0, 17:0, and trans-16:1n-7 as biomarkers of dairy fat intake in recent observational studies that suggest beneficial effects of dairy food on incidence of diabetes and stroke. The American Journal of Clinical Nutrition, 2015 (letter)
- Dairy Fat Intake, Plasma Pentadecanoic Acid, and Plasma Iso-heptadecanoic Acid Are Inversely Associated With Liver Fat in Children. Journal of Pediatric Gastroenterology and Nutrition, 2021 (observational)
- Plasma pentadecanoic acid is modestly related to cardiovascular health in CARDIA and ARIC cohorts: observational associations without evidence of causality. Frontiers in Nutrition, 2026
- Broader and safer clinically-relevant activities of pentadecanoic acid compared to omega-3: Evaluation of an emerging essential fatty acid across twelve primary human cell-based disease systems. PLOS ONE, 2022 (cell-based study)
- Catabolism of Branched Chain Amino Acids Contributes Significantly to Synthesis of Odd-Chain and Even-Chain Fatty Acids in 3T3-L1 Adipocytes. PLoS One, 2015 (cell-based study)
- Wu Y et al. Odd Chain Fatty Acids Are Not Robust Biomarkers for Dietary Intake of Fiber. Molecular nutrition & food research (2021). PMID 34605164
- Kamalita Pertiwi et al. Associations of dairy and fiber intake with circulating odd-chain fatty acids in post-myocardial infarction patients. Nutrition & Metabolism (2019). PMID 31754368
- Sellem L et al. Can individual fatty acids be used as functional biomarkers of dairy fat consumption in relation to cardiometabolic health? A narrative review. The British journal of nutrition (2022). PMID 35086579
- Liang Sun et al. Erythrocyte odd-chain fatty acids and the risk of cardiometabolic diseases: a prospective study and updated meta-analysis. European Journal of Preventive Cardiology (2025). PMID 40987456
- Peng W et al. The causal relationship of human blood metabolites with the components of Sarcopenia: a two-sample Mendelian randomization analysis. BMC geriatrics (2024). PMID 38622574
- Qian Z et al. Metabolic clues to aging: exploring the role of circulating metabolites in frailty, sarcopenia and vascular aging related traits and diseases. Frontiers in genetics (2024). PMID 38415056
- Huang L et al. Circulating Saturated Fatty Acids and Incident Type 2 Diabetes: A Systematic Review and Meta-Analysis. Nutrients (2019). PMID 31052447
- Chen X et al. Lipid biomarkers for the prediction of type 2 diabetes risk, an umbrella review and updated meta-analyses of prospective observational studies. Frontiers in endocrinology (2026). PMID 42181198
- Marcela Prada et al. Association of the odd-chain fatty acid content in lipid groups with type 2 diabetes risk: A targeted analysis of lipidomics data in the EPIC-Potsdam cohort. Clinical Nutrition (2021). PMID 34364238
- Cinelli G et al. Association between Maternal and Foetal Erythrocyte Fatty Acid Profiles and Birth Weight. Nutrients (2018). PMID 29570689
- Thiébaut AC et al. Correlation between serum phospholipid fatty acids and dietary intakes assessed a few years earlier. Nutrition and cancer (2009). PMID 19838922
Want the detail behind the numbers? See our C15:0 research statistics page and the 2024 C15:0 supplement trial, explained.
Frequently Asked Questions
What foods are highest in C15?
Full-fat dairy products (butter, whole milk, cream, and aged cheeses) are the most consistent dietary sources of C15. Fatty marine fish and some fermented foods also contain detectable amounts. The C15 content of dairy varies with the animal’s diet, tending to be higher in grass-fed versus grain-fed ruminants.
Is C15 the same as a standard saturated fat?
C15 is technically a saturated fat, but its odd-chain length sets it apart from the more studied even-chain saturated fats like palmitic acid (C16:0) or stearic acid (C18:0). The body metabolizes odd-chain and even-chain fats through somewhat different pathways, and their associations with health markers in epidemiological research have not always pointed in the same direction.

How does C15 differ from omega-3 fatty acids?
C15 is an odd-chain saturated fat from dairy and ruminant fat, while EPA and DHA are long-chain polyunsaturated fats from fish and algae, and the omega-3 family is an established essential nutrient. In a cell-based study, C15 shared some activities with EPA and had additional anti-inflammatory ones, but that work was done in cultured cells by authors with patent interests in C15, and it has not been tested head to head in people.[13]
Has the FDA approved C15 for any health condition?
No. The FDA has not evaluated C15 supplements for the treatment, prevention, or cure of any disease or health condition. C15 products are sold as dietary supplements, not drugs, and are not subject to the same pre-market approval requirements as pharmaceuticals.
What does 'partial PPAR agonism' mean in plain language?
PPAR-α and PPAR-δ are proteins inside cells that act like molecular switches, turning on genes involved in fat metabolism and inflammation regulation. A ‘partial agonist’ activates these switches at a moderate level rather than fully. Researchers propose this partial activation profile may be biologically meaningful without the side effects associated with full pharmaceutical PPAR agonists, but this comparison has not been tested in head-to-head clinical trials.
Can I get enough C15 from eating dairy instead of taking a supplement?
Dairy fat does provide C15, and for people who consume full-fat dairy regularly, it is a natural source of this fatty acid. Whether the amounts obtained from typical dairy consumption equal the doses studied in supplementation research is not clearly established. Individuals who avoid dairy or follow low-fat diets will have lower dietary exposure to C15.
Are there any known risks or side effects from C15 supplementation?
The one published supplement trial (200 mg/day) reported no significant adverse events [1]. However, the studies conducted to date have been small and relatively short-term, so a comprehensive long-term safety profile does not yet exist. Anyone with chronic health conditions, those taking lipid-modifying medications, or those who are pregnant or breastfeeding should speak with a healthcare provider before supplementing.
These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease. Content is for informational purposes only and is not medical advice; consult a qualified healthcare provider before starting any supplement. As an Amazon Associate we earn from qualifying purchases.